







The three main skin cancer types are basal cell carcinoma, squamous cell carcinoma and melanoma. BCC rarely spreads, SCC can spread, while melanoma has greater potential to spread.
Skin cancer types are usually grouped into melanoma and non-melanoma skin cancer. The non-melanoma group includes basal cell carcinoma (BCC) and squamous cell carcinoma (SCC). Although these cancers all develop from abnormal skin cells, they start in different types of cells and can look and behave quite differently.
Key Takeaways
- BCC grows from basal cells and usually remains localised to the skin.
- SCC develops from squamous cells and carries a small risk of spreading.
- Melanoma begins in melanocytes and has greater potential to spread.
- UV exposure is a major preventable risk factor across all three.
What Is Skin Cancer?
Skin cancer develops when cells in the skin begin growing abnormally and continue dividing when they should stop. The type of skin cancer depends on the kind of skin cell affected.
Broadly, skin cancers fall into two groups. Melanoma develops from melanocytes, the cells responsible for producing skin pigment. Non-melanoma skin cancer mainly refers to basal cell carcinoma and squamous cell carcinoma, which develop from different cells within the epidermis.
Skin cancers are collectively the most commonly diagnosed cancers in the UK. That figure covers a wide range of cancers with very different levels of risk, so understanding the individual types is more useful than treating skin cancer as one condition.
What Does BCC Look Like (and How Does It Develop)?
Basal cell carcinoma is the most common form of skin cancer in the UK and makes up the large majority of cases. It usually develops slowly, often on parts of the body that receive regular UV exposure such as the face, ears, scalp and neck.
Where Basal Cell Carcinoma Begins
BCC develops from basal cells, which are found in the deepest part of the epidermis. These cells continually divide to replace older skin cells as they move towards the skin surface.
When abnormal changes occur in basal cells, the resulting cancer can gradually grow within the surrounding tissue. This is why BCC often starts as a relatively small lesion and changes over a longer period rather than appearing suddenly.
Typical Appearance
BCC does not have one fixed appearance. It can look like a slow growing lump, sore or patch that fails to heal properly. Some lesions are pearly, shiny or waxy, while others appear pink, red or close to the colour of normal skin.
A BCC may also develop crusting, bleeding or a small ulcer. Some types are less obvious and can resemble a flat, slightly scar-like area rather than a conventional growth.
How BCC Commonly Behaves
BCC typically grows slowly and rarely spreads beyond the skin. Its main problem is local growth, as an untreated tumour can continue extending into nearby tissue.
The way a lesion looks cannot confirm whether it is BCC. A sore, lump or patch that persists or keeps changing should be professionally assessed. Our mole checking service provides specialist assessment for people concerned about an unusual or changing mole.
What Is Squamous Cell Carcinoma (SCC)?
Squamous cell carcinoma develops from squamous cells within the upper layers of the epidermis. It is the second most common type of non melanoma skin cancer in the UK and is strongly associated with cumulative exposure to ultraviolet radiation.
Where Squamous Cell Carcinoma Begins
SCC begins in squamous cells, which form much of the outer layer of the skin and help create its protective barrier.
Abnormal growth in these cells can produce a lesion that gradually becomes thicker, more raised or more irregular. SCC often develops on areas exposed to the sun, including the face, ears, scalp, lips and backs of the hands.
Typical Appearance
SCC can appear as a firm, raised lesion with a rough, scaly or crusted surface. It may begin as a persistent rough patch before becoming thicker or more inflamed.
As it develops, an SCC may become:
- More raised
- Red or inflamed
- Tender or sore
- Crusted or scaly
- Prone to bleeding
The appearance can overlap with harmless skin conditions, particularly in its earlier stages. A persistent scaly patch or firm lesion that continues to change therefore deserves professional assessment.
How SCC Commonly Behaves
SCC behaves differently from BCC because it carries a small but real risk of spreading to other parts of the body. The likelihood varies according to the characteristics and location of the individual tumour.
That risk is one reason suspicious SCC should not simply be left to monitor indefinitely. A clinician can assess the lesion and decide whether it needs further testing or treatment.
How Does Melanoma Develop?
Melanoma develops from melanocytes, the pigment producing cells in the skin. It is less common than BCC and SCC, but it has a greater tendency to spread, which makes changes in existing moles and new pigmented marks particularly important.
Where Melanoma Begins
Melanoma begins in melanocytes, which produce melanin and help determine the colour of the skin, hair and eyes. It can develop inside an existing mole or appear as a new mark on previously normal skin.
This means melanoma is not restricted to people with a large number of moles. A new pigmented mark that looks noticeably different from the surrounding skin can also warrant assessment.
Typical Appearance
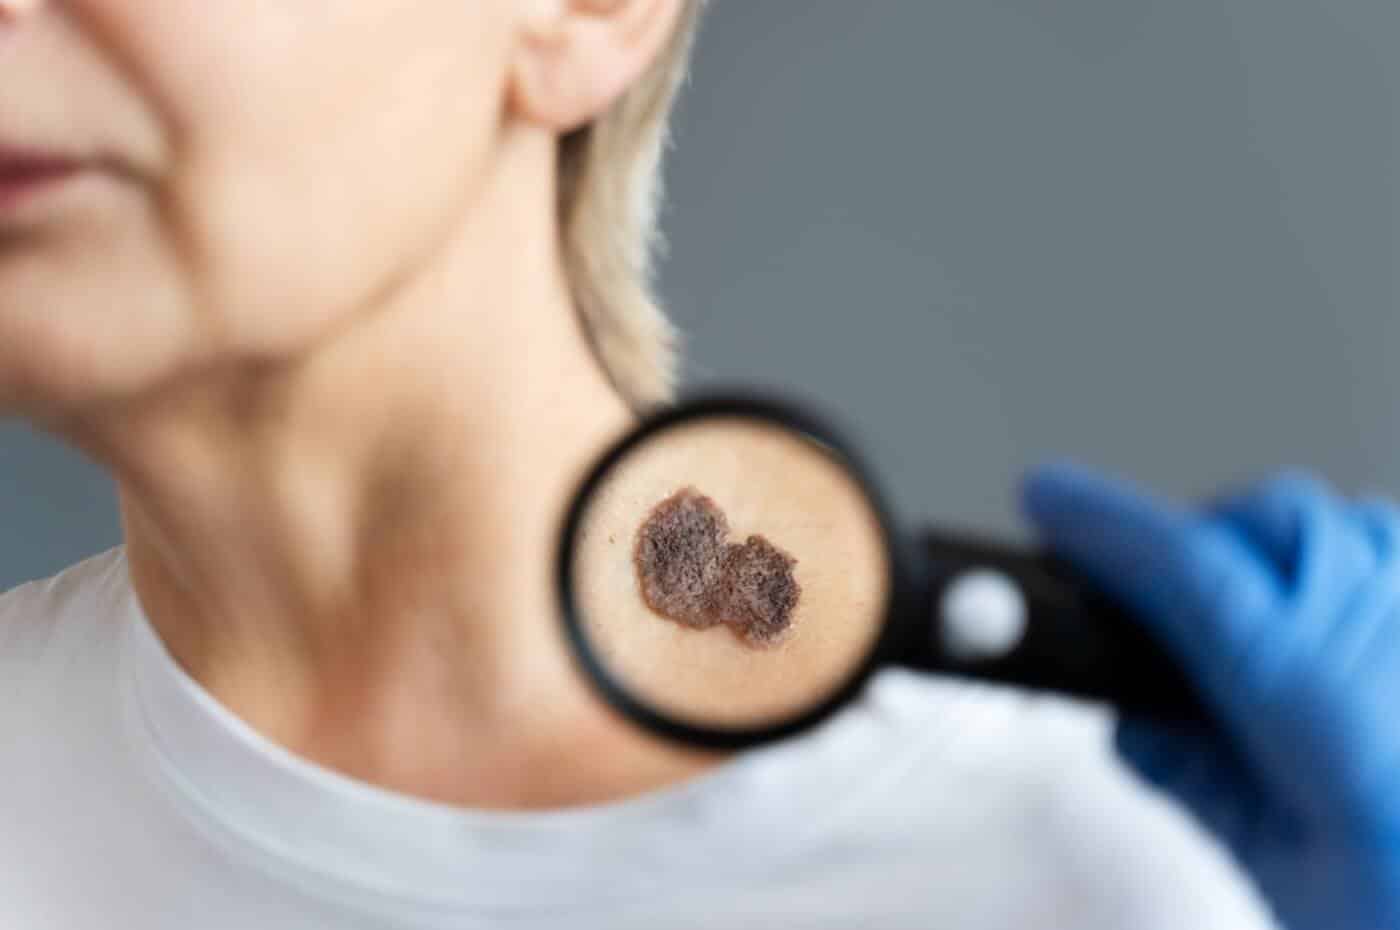
Melanoma often attracts attention because a mole begins to change in size, shape, border or colour. The colour may become uneven or contain several different shades within the same lesion. One side may also look different from the other, while the edge becomes irregular or less clearly defined.
A completely new dark mark can be another warning sign, particularly when it looks different from a person’s other moles.
Appearance alone cannot establish that a lesion is melanoma. A changing mole or unusual pigmented mark should be assessed rather than judged against photographs or descriptions online.
How Melanoma Commonly Behaves
Melanoma is less common than basal cell carcinoma (BCC) or squamous cell carcinoma (SCC), but it has a greater potential to spread to nearby tissues or other parts of the body. This is why a suspicious lesion that could be melanoma should be assessed promptly rather than monitored without professional advice.
According to Cancer Research UK, melanoma is the fifth most common cancer in the UK, accounting for around 5% of all new cancer cases. Around 86% of melanoma skin cancer cases in the UK are caused by overexposure to ultraviolet (UV) radiation.
Melanoma can develop on previously normal skin or within an existing mole. Changes in a mole, a new unusual mark or a lesion that continues to change can therefore warrant assessment, particularly when its appearance differs from your other moles.
How Do the Three Types Compare?
BCC, SCC and melanoma can all be linked to UV exposure, but their usual patterns of growth and spread are different.
The infographic below gives a general comparison rather than a way to identify an individual lesion:
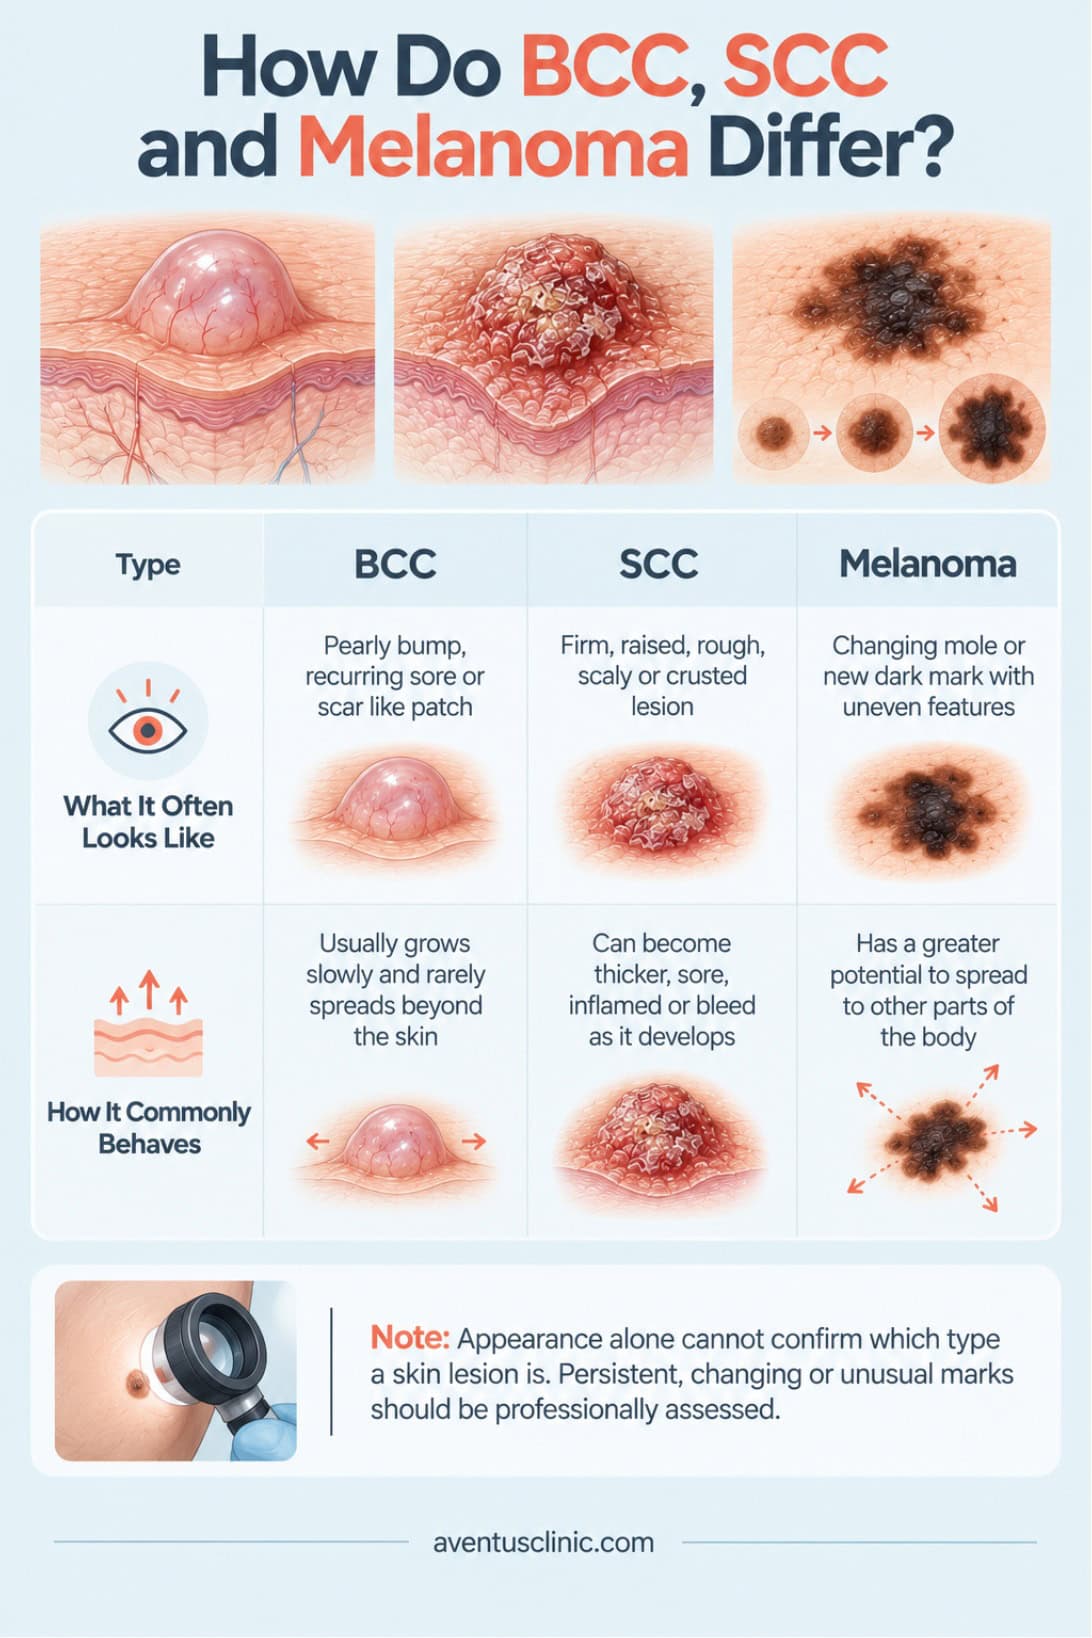
The biggest difference is how cancers tend to behave. BCC usually remains within the skin, SCC has some potential to spread and melanoma has a greater tendency to spread beyond its original site.
Why Are Skin Cancer Rates Rising in the UK?
Skin cancer rates in the UK have risen for several reasons. The main factors behind this increase include:
- Cumulative UV damage from repeated exposure over many years
- Episodes of sunburn that can cause lasting DNA damage in skin cells
- Past sunbed use that exposed people to concentrated UV radiation
- An ageing population that increases the number of people in higher risk age groups
- Earlier diagnosis that means more cases are identified and recorded
Holiday travel has played a role too. More people began taking overseas holidays in sunnier climates, which increased exposure to intense UV radiation. The effects can build over many years, so exposure earlier in life can contribute to skin cancer later on.
The increase in non melanoma skin cancer is particularly pronounced over a longer period. UK figures show a 169% rise since the early 1990s and an increase of more than two fifths over the last decade.
An ageing population also affects these figures. Skin cancer becomes more common as people get older. Better awareness, diagnosis and reporting may also contribute to the rise.
What Causes Skin Cancer?
Ultraviolet radiation is the main known modifiable risk factor across the three major skin cancer types. UV from sunlight can damage the DNA within skin cells, and repeated exposure over time increases the chance of abnormal cell changes.
The link is particularly strong for melanoma. Around 86% of melanoma skin cancer cases in the UK are estimated to be attributable to overexposure to UV radiation.
Sunbeds also expose the skin to UV radiation and are another avoidable source of exposure. Using a sunbed before age 20 has been associated with a 47% higher risk of melanoma compared with never using one, while the World Health Organization classifies sunbeds as a Group 1 carcinogen.
UK law also places restrictions on their use. The Sunbeds (Regulation) Act 2010 prohibits people under 18 from using or being offered access to commercial sunbeds.
UV exposure is not the only factor involved in skin cancer. Age, individual susceptibility and other characteristics can influence risk too, so reducing UV exposure lowers risk without eliminating it completely.
How Is Skin Cancer Assessed and Diagnosed?
A clinician will usually begin by examining the skin lesion and the surrounding area. Dermoscopy may be used to look at structures beneath the surface that are not easily visible to the naked eye.
When a lesion remains suspicious, further investigation may be needed. A biopsy can allow tissue to be examined under a microscope and can confirm whether cancer is present and, where relevant, which type it is.
The urgency of referral differs between the three major skin cancer types. NICE referral guidance for suspected skin cancer recommends urgent referral pathways for suspected melanoma and SCC. Suspected BCC is generally managed through routine referral unless delaying treatment could have a significant impact because of factors such as the tumour’s size or location.
Treatment decisions then depend on the individual cancer. Factors such as the tumour’s risk category, location, size and the person’s circumstances can affect which treatment is appropriate.
A skin cancer screening appointment can provide a specialist examination when a mole, lump, sore or other skin change needs further assessment.
Why Early Assessment Matters
Early assessment can establish what a suspicious skin change actually represents before it has more time to develop. This matters because the three main skin cancer types do not carry the same risk or follow the same treatment pathway.
A changing skin lesion can have several possible causes:
- A benign mole
- Melanoma
- Another skin condition
- Basal cell carcinoma
- Squamous cell carcinoma
The appearance alone cannot reliably tell you which condition is responsible.
Professional assessment also means the lesion can be considered in context rather than judged against a generic description. The clinician can examine its appearance, structure, history and any changes that have occurred over time.
Getting an unusual skin change checked does not mean that cancer will be found. It means you have a clearer answer about what the lesion is and whether anything further needs to be done.
FAQs
What is the most common type of skin cancer in the UK?
Basal cell carcinoma is the most common type of skin cancer in the UK. It accounts for the large majority of skin cancer cases and rarely spreads beyond the skin.
Which type of skin cancer is most serious?
Melanoma has greater potential to spread than BCC or SCC. This is why a suspicious melanoma requires prompt clinical assessment.
Can basal cell carcinoma spread?
Yes, although spread is rare. BCC can still grow into surrounding tissue and cause significant local damage if it is not treated.
Is squamous cell carcinoma dangerous?
SCC can spread to other parts of the body, although the risk is relatively small. The behaviour of an individual tumour depends on its characteristics.
Can skin cancer be prevented?
Not every case can be prevented, but reducing UV exposure can lower risk. Sun protection and avoiding sunbeds are important steps.
Conclusion
BCC, SCC and melanoma develop from different skin cells and can behave very differently. BCC usually remains localised, SCC carries some risk of spread, and melanoma has greater potential to spread. Any unusual or changing skin lesion deserves professional assessment rather than self-diagnosis. Book a skin check with our GMC-registered dermatology team for expert assessment and peace of mind.
Medical Disclaimer: The information in this article is for general educational purposes only and is not medical advice, diagnosis or treatment. Skin cancer can appear in different ways, and appearance alone cannot confirm cancer. If you notice a new or changing lesion, persistent sore, bleeding or unusual mark, seek advice from a qualified healthcare professional.

Concerned about a mole, lesion or unusual skin change? Get a professional assessment from our clinical team and clear guidance on the most appropriate next steps.


 CALL US
 WHATSAPP